
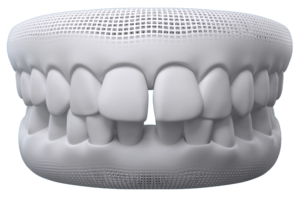
What Causes Gaps Between Teeth?
Dental spacing, clinically called diastema, is any excess space between adjacent teeth. The gap between the two upper central incisors (the midline diastema) is the most visible, but gaps can appear anywhere in the arch. About 98% of six-year-olds have a midline diastema that closes naturally as permanent teeth come in.
By ages 12 to 18, only about 7% still have a gap. In adults, spacing does not close on its own and often widens with time, especially under the forces of chewing, tongue posture, or tissue changes around the teeth.
The first question at a Bold Bite consultation is not “braces or aligners?” It is “why is the space there?” Dr. Marty and Dr. Cao evaluate tooth size, jaw size, frenum anatomy, tongue posture, periodontal health, and family history before recommending any mechanics.
The reason matters because the treatment plan. And often whether orthodontics alone is enough. Depends entirely on the cause.
Diastema vs. Generalized Spacing
“Diastema” technically means any gap, but in everyday use it refers to the single space between the two upper front teeth. “Generalized spacing” is the term for gaps distributed throughout one or both arches.
Midline Diastema
A single, visible gap between the upper central incisors. Causes include an oversized or low-attached labial frenum, a supernumerary tooth (often a mesiodens) wedged between the roots, missing or peg-shaped lateral incisors that allow the centrals to drift, or a tooth-size discrepancy.
Children often have a midline diastema that closes on its own once the upper canines erupt, the so-called “ugly duckling stage.”
Generalized Spacing
Smaller gaps spread across several teeth in the arch. Usually caused by a tooth-to-jaw size mismatch (normal-sized teeth in a larger-than-average jaw), by genuine microdontia (smaller-than-average teeth), or by pathologic migration where gum disease has loosened periodontal support.
Generalized spacing in an adult whose teeth were previously aligned is a signal to rule out periodontal bone loss before starting any orthodontic movement.
Common Causes and How Each Is Treated
Not all gaps are the same. The cause determines whether the gap is cosmetic, functional, or a warning sign of something more serious.
Jaw-Tooth Size Mismatch
The most common cause. The jaw is larger than the combined width of the teeth, a genetic trait often inherited from parents. Teeth are normal size, but there is simply too much room. Gaps appear evenly throughout the arch (generalized spacing).
Treatment at Bold Bite: Braces or Angel Aligners close the spaces by redistributing the teeth evenly across the arch. The decision between aligners and braces is made with the patient, not for the patient. Dr. Marty and Dr. Cao present the pros and cons of each and let the family own the choice, weighing in only for specific clinical reasons.
Oversized or Low-Attached Labial Frenum
The labial frenum, the fold of tissue connecting the inside of the upper lip to the gum above the front teeth, sometimes extends between and under the two central incisors. This band of tissue physically holds the gap open and will reopen a closed gap if it is not released.
Treatment: Frenectomy (a minor soft-tissue release, typically performed by an oral surgeon or pediatric dentist) followed by orthodontic space closure. In younger children, the gap sometimes closes on its own after a frenectomy. In adults, orthodontic closure is almost always needed after the release.
Missing, Peg, or Undersized Lateral Incisors
Peg laterals (developmentally narrow upper lateral incisors) and congenitally missing laterals are the second most common cause of midline diastema. The centrals drift into the widened space where the lateral should sit.
Treatment: A coordinated plan. Orthodontics positions the teeth into their ideal final positions first, then a restorative dentist completes the smile with bonding, porcelain veneers, or. Where a tooth is missing entirely.
An implant. Bold Bite Orthodontics coordinates these cases with the patient’s general or cosmetic dentist from day one so the final tooth dimensions are planned before orthodontic movement begins, not improvised afterward.
Tongue Thrust or Thumb Sucking
Forward pressure from a tongue thrust, a persistent thumb-sucking habit, or chronic mouth breathing pushes the front teeth apart. These patients often present with both spacing and an open bite at the same time, because the same forward pressure prevents the upper and lower incisors from meeting.
Treatment: Address the habit first, either with myofunctional therapy exercises or an appliance that discourages the thrust, then close the gaps with braces or aligners. Skipping the habit work almost guarantees relapse.
Periodontal Disease (Pathologic Migration)
When gum disease erodes the bone supporting the teeth, they lose their anchor and begin to drift apart. This is called pathologic migration. New or widening gaps in adults, particularly in the lower front teeth, can be an early warning that periodontal disease is active.
When gaps are a warning sign: A gap that appears or widens in adulthood. Especially with bleeding gums, loose teeth, or receding gumlines. May indicate active periodontal disease. Dr. Marty’s 8-plus years in general dentistry prior to orthodontic specialization gave them a clinical eye for caries and periodontal risk that is screened at every Bold Bite consult. No orthodontic movement begins until periodontal stability is confirmed, moving teeth through diseased bone accelerates bone loss.
When Spacing Is Not a Problem
Healthy spacing in children: Gaps between baby teeth are not only normal, they are desirable. Primate spaces between the baby incisors and canines mean there is room for the larger permanent teeth coming in behind them. A tight, gap-free set of baby teeth is often the earlier signal of crowding, not the spaced set.
Two spacing patterns routinely seen at Bold Bite that usually resolve without treatment:
At the AAO-recommended age-seven evaluation, Dr. Marty and Dr. Cao screen for the spacing patterns that do require intervention, oversized frenums, supernumerary teeth, missing laterals, while reassuring families when the spacing they are seeing is developmental and expected. Not every gap needs treatment; knowing which ones do is the value of a specialist evaluation.
How Bold Bite Closes Gaps
Spacing cases are among the most aligner-friendly orthodontic conditions because the teeth are moving into open space rather than competing for room. That said, the best treatment depends on what is causing the gap, how much space is involved, and whether the bite also needs correction. Dr. Marty and Dr. Cao match the mechanics to the diagnosis.
| Treatment | Best For | How It Works | Starting Price |
|---|---|---|---|
| Angel Aligners ← Primary aligner at Bold Bite | Mild to moderate spacing; diastema closure; adults and teens | Sequential aligners planned on iOrtho software; stiffer material than Invisalign for more efficient space closure | See current fees |
| Invisalign |
Mild to moderate spacing; patients who prefer the Invisalign brand
|
Sequential aligners move teeth into gaps. Removable. Nearly invisible
|
See current fees
|
| Metal Braces |
Generalized spacing combined with bite correction; complex root control
|
Archwire forces close gaps with precise control of root position. CBCT-verified finishing
|
See current fees
|
| Clear Ceramic Braces |
Generalized spacing with an aesthetic preference for fixed appliances
|
Same mechanics as metal with tooth-colored, self-ligating brackets
|
See current fees
|
| Frenectomy + Orthodontics |
Midline diastema caused by an oversized frenum
|
Minor soft-tissue release by an oral surgeon or pediatric dentist, followed by orthodontic space closure
|
Frenectomy billed separately; ortho fees are on our braces cost page
|
| Orthodontics + Restorative |
Peg laterals or congenitally missing teeth
|
Orthodontics positions teeth into their planned final positions, then bonding, veneers, or implants complete the smile
|
Ortho: see current fees; restorative varies
|
For cases that involve both spacing and a bite problem (deep bite, open bite, or crossbite), braces often move treatment along more efficiently than aligners. For isolated diastema or generalized spacing without significant bite issues, aligners are typically the preferred mechanic.
Especially Angel Aligners, which Dr. Marty and Dr. Cao have adopted as the primary clear-aligner system at Bold Bite after direct in-office comparison against Invisalign on the same patients.
The Bold Bite Approach to Retention After a Diastema
Spacing has the highest relapse rate of any orthodontic correction. The elastic fibers in the gum tissue retain a “memory” of the original tooth position for years, which means a closed gap will slowly reopen the moment retainer wear lapses. Dr. Marty and Dr. Cao treat retention as the second half of the treatment plan, not an afterthought.
Bold Bite includes two sets of Essix retainers with every case. Every comprehensive patient finishes with two sets of retainers and automatic enrollment in Retainer Club, so a replacement is always a tap away. Through Retainer Club, patients reorder a fresh set anytime from their phone at a reduced member rate, or join the Smile Care plan, which lowers that cost further and ships a new retainer once a year for as long as they stay enrolled.
Fixed (bonded) retainers are offered only when clinically indicated. For upper midline diastema cases where the labial frenum has been released but the soft tissue is thick, a small bonded wire behind the upper front teeth is sometimes added to the Essix protocol to prevent the two centrals from drifting apart again.
When a fixed retainer is used, the wire is kept as small as possible and a clear Essix is still recommended on top of it. The default at Bold Bite remains removable retention.
Why Retention Compliance Is Critical for Spacing Cases
Essix retainers at Bold Bite are fabricated on 3D-printed models of the final tooth positions, a tighter and more precise fit than retainers thermoformed on stone models. That precision matters most for spacing cases, because even a fraction of a millimeter of slippage over months translates into a visible gap.
The wear protocol after a diastema or spacing correction is straightforward: 12 hours a day for the first six months (sleeping, plus a few additional hours), switching to nighttime-only if the teeth are stable at the 6-month check, and nighttime wear indefinitely thereafter. Retainers stay at home.
Never in a pocket at lunch, never wrapped in a napkin on a restaurant table. Lost retainers are the leading cause of spacing relapse, not failed mechanics.
Gaps in Children’s Teeth: When to Monitor, When to Treat
Most childhood spacing is developmental and self-correcting. The question for parents is not “is there a gap?” but “is the gap the kind that will close on its own, or the kind that will not?”
When the gap will usually close on its own: A midline diastema in a six- to nine-year-old with unerupted upper canines, primate spaces in the baby teeth, or generalized spacing across a set of primary teeth that are clearly smaller than the permanent teeth on the way.
When an evaluation is warranted: The gap persists after the upper canines have fully erupted (typically by age 12 to 13), the gap is larger than 3 mm, a single tooth is noticeably smaller than its twin on the other side of the arch (possible peg lateral), or an adult tooth is missing on panoramic imaging. Dr. Marty uses 3D CBCT imaging to determine whether the gap is caused by an oversized frenum, missing lateral incisors, a supernumerary tooth (such as a mesiodens) blocking closure, or simply a tooth-size discrepancy in one visit, rather than discovering a second problem halfway through treatment.
The AAO recommends a first orthodontic evaluation by age 7, not to start treatment, but to monitor development and identify any underlying issues early enough to plan for. At Bold Bite, approximately three-quarters of children evaluated at that age are placed on growth recall rather than moved into active treatment. The consultation itself is free.
Typical Treatment Timeline
| Stage | Duration | What Happens |
|---|---|---|
| Records & diagnosis | 1 visit | iTero and Allied Star digital scan, intraoral photos, periodontal screening, cause identification, 3D CBCT if needed |
| Periodontal treatment (if indicated) |
Before ortho
|
Coordinated with the patient’s general dentist or periodontist before any tooth movement
|
| Frenectomy (if indicated) |
1 visit
|
Released by an oral surgeon or pediatric dentist; healing before ortho
|
| Aligner or braces treatment |
6–18 months
|
Controlled space closure; generalized spacing 12–18 months, isolated diastema often less
|
| Restorative phase (if peg laterals or missing teeth) |
After active ortho
|
Bonding, veneers, or implants to complete the smile
|
| Retention |
Indefinite
|
Two Essix sets included, plus a bonded wire when indicated for upper diastema
|
What to Expect at a Spacing Consultation
Before & After
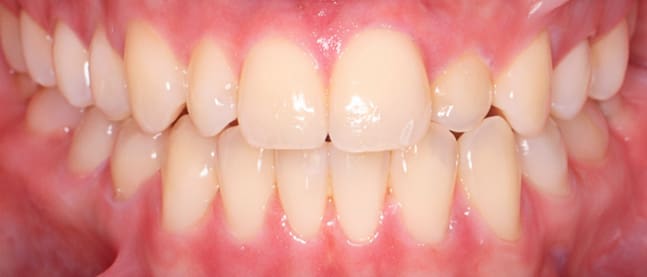
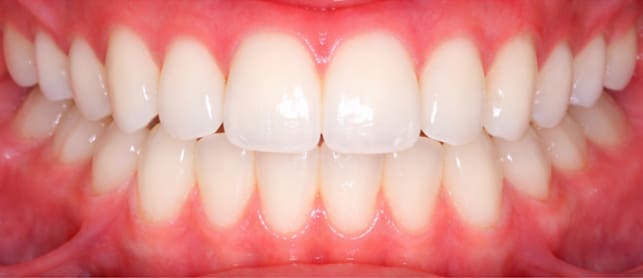
Crowding: Invisalign/Clear Aligners
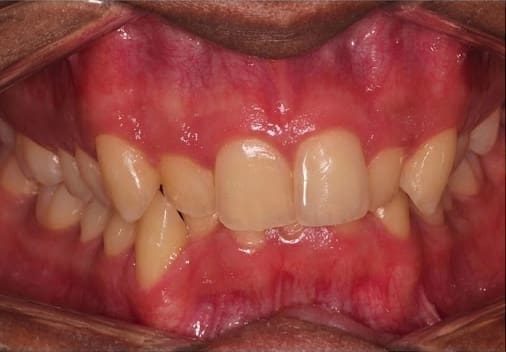
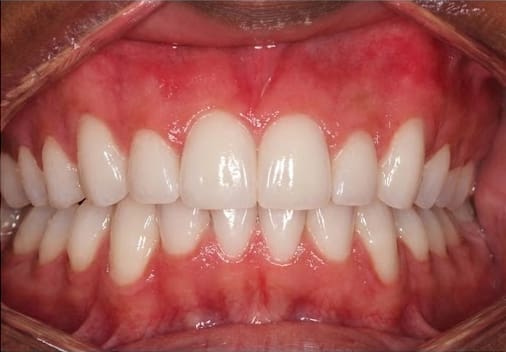
Deep Overbite: Braces with Bite-Pads
See more spacing cases in the Limestone Hills treated-cases gallery.
How Much Does It Cost to Close Gaps in Jacksonville?
Spacing-only cases with no bite issues may qualify for limited (partial) treatment at a lower fee. This is determined at the free consultation.
Pricing at Bold Bite reflects specialist-level diagnosis, personalized treatment planning, and the tools used. 3D CBCT, iTero and Allied Star digital scanning, in-house 3D printing, CBCT-integrated aligner setups, and Grin Scope remote monitoring are included as standard rather than as upcharges.
Two orthodontists in one office, unhurried appointments and a higher standard of finish. The model is not volume-based.
Insurance & Financing
Most PPO dental insurance covers orthodontic treatment when spacing is documented as malocclusion. Bold Bite verifies benefits before treatment begins. In-House 0% APR: 0% interest, no credit check, a down payment, then monthly payments.
Cherry: financing subject to credit approval; terms vary. Pay in Full: pay-in-full discount.
Common Appliances Used at Bold Bite
Simple spacing and gaps respond well to clear aligners, which close the space while the patient avoids brackets and wires. For midline diastema with a thick frenum, Dr. Marty or Dr. Cao relies on a fixed bonded retainer above the Essix to hold the closure long-term.
Frequently Asked Questions
Can Bold Bite close a gap with Invisalign?
Dr. Marty and Dr. Cao typically recommend Angel Aligners as the primary aligner at Bold Bite after running a direct head-to-head comparison on the same patients, but Invisalign remains a strong option for patients who prefer that brand.
Will my gaps come back after treatment?
For upper midline diastema cases with a thick labial frenum, a small bonded wire behind the upper front teeth is often added to the Essix protocol to lock in the result.
